Answers written by Mr Tofunmi Oni, Consultant Orthopaedic Surgeon (MBChB BSc PGDip FRCS (Tr & Orth), GMC 7074916), who treats knee osteoarthritis with everything from exercise advice and injections to partial and total knee replacement. Figures come from NICE, the NHS, Versus Arthritis, Cochrane and the studies listed in the sources at the end. Last reviewed October 2026.
How can I tell if my knee pain is arthritis or something else?
Osteoarthritis typically causes activity related pain in someone over 45 with little or no morning stiffness, under 30 minutes. NICE says it can be diagnosed on those features alone, without an X ray. Longer morning stiffness, a hot swollen joint or symmetrical involvement of small joints point to inflammatory arthritis; sudden severe pain with hot red skin suggests gout or infection; locking or giving way suggests a meniscal tear; and knee pain with a normal knee examination is sometimes referred from the hip.
Is knee arthritis diagnosed with an X ray or MRI?
Neither is needed in the typical case. NICE says not to use imaging routinely unless there are atypical features: recent trauma, prolonged morning stiffness, rapid worsening or deformity, a hot swollen joint, or concern about infection or cancer. When imaging is used, a standing X ray is the standard test. MRI is used less often and mainly for soft tissue problems; it is not a good way to grade arthritis and tends to find incidental things that worry people.
What is bone on bone, and what can be done about it?
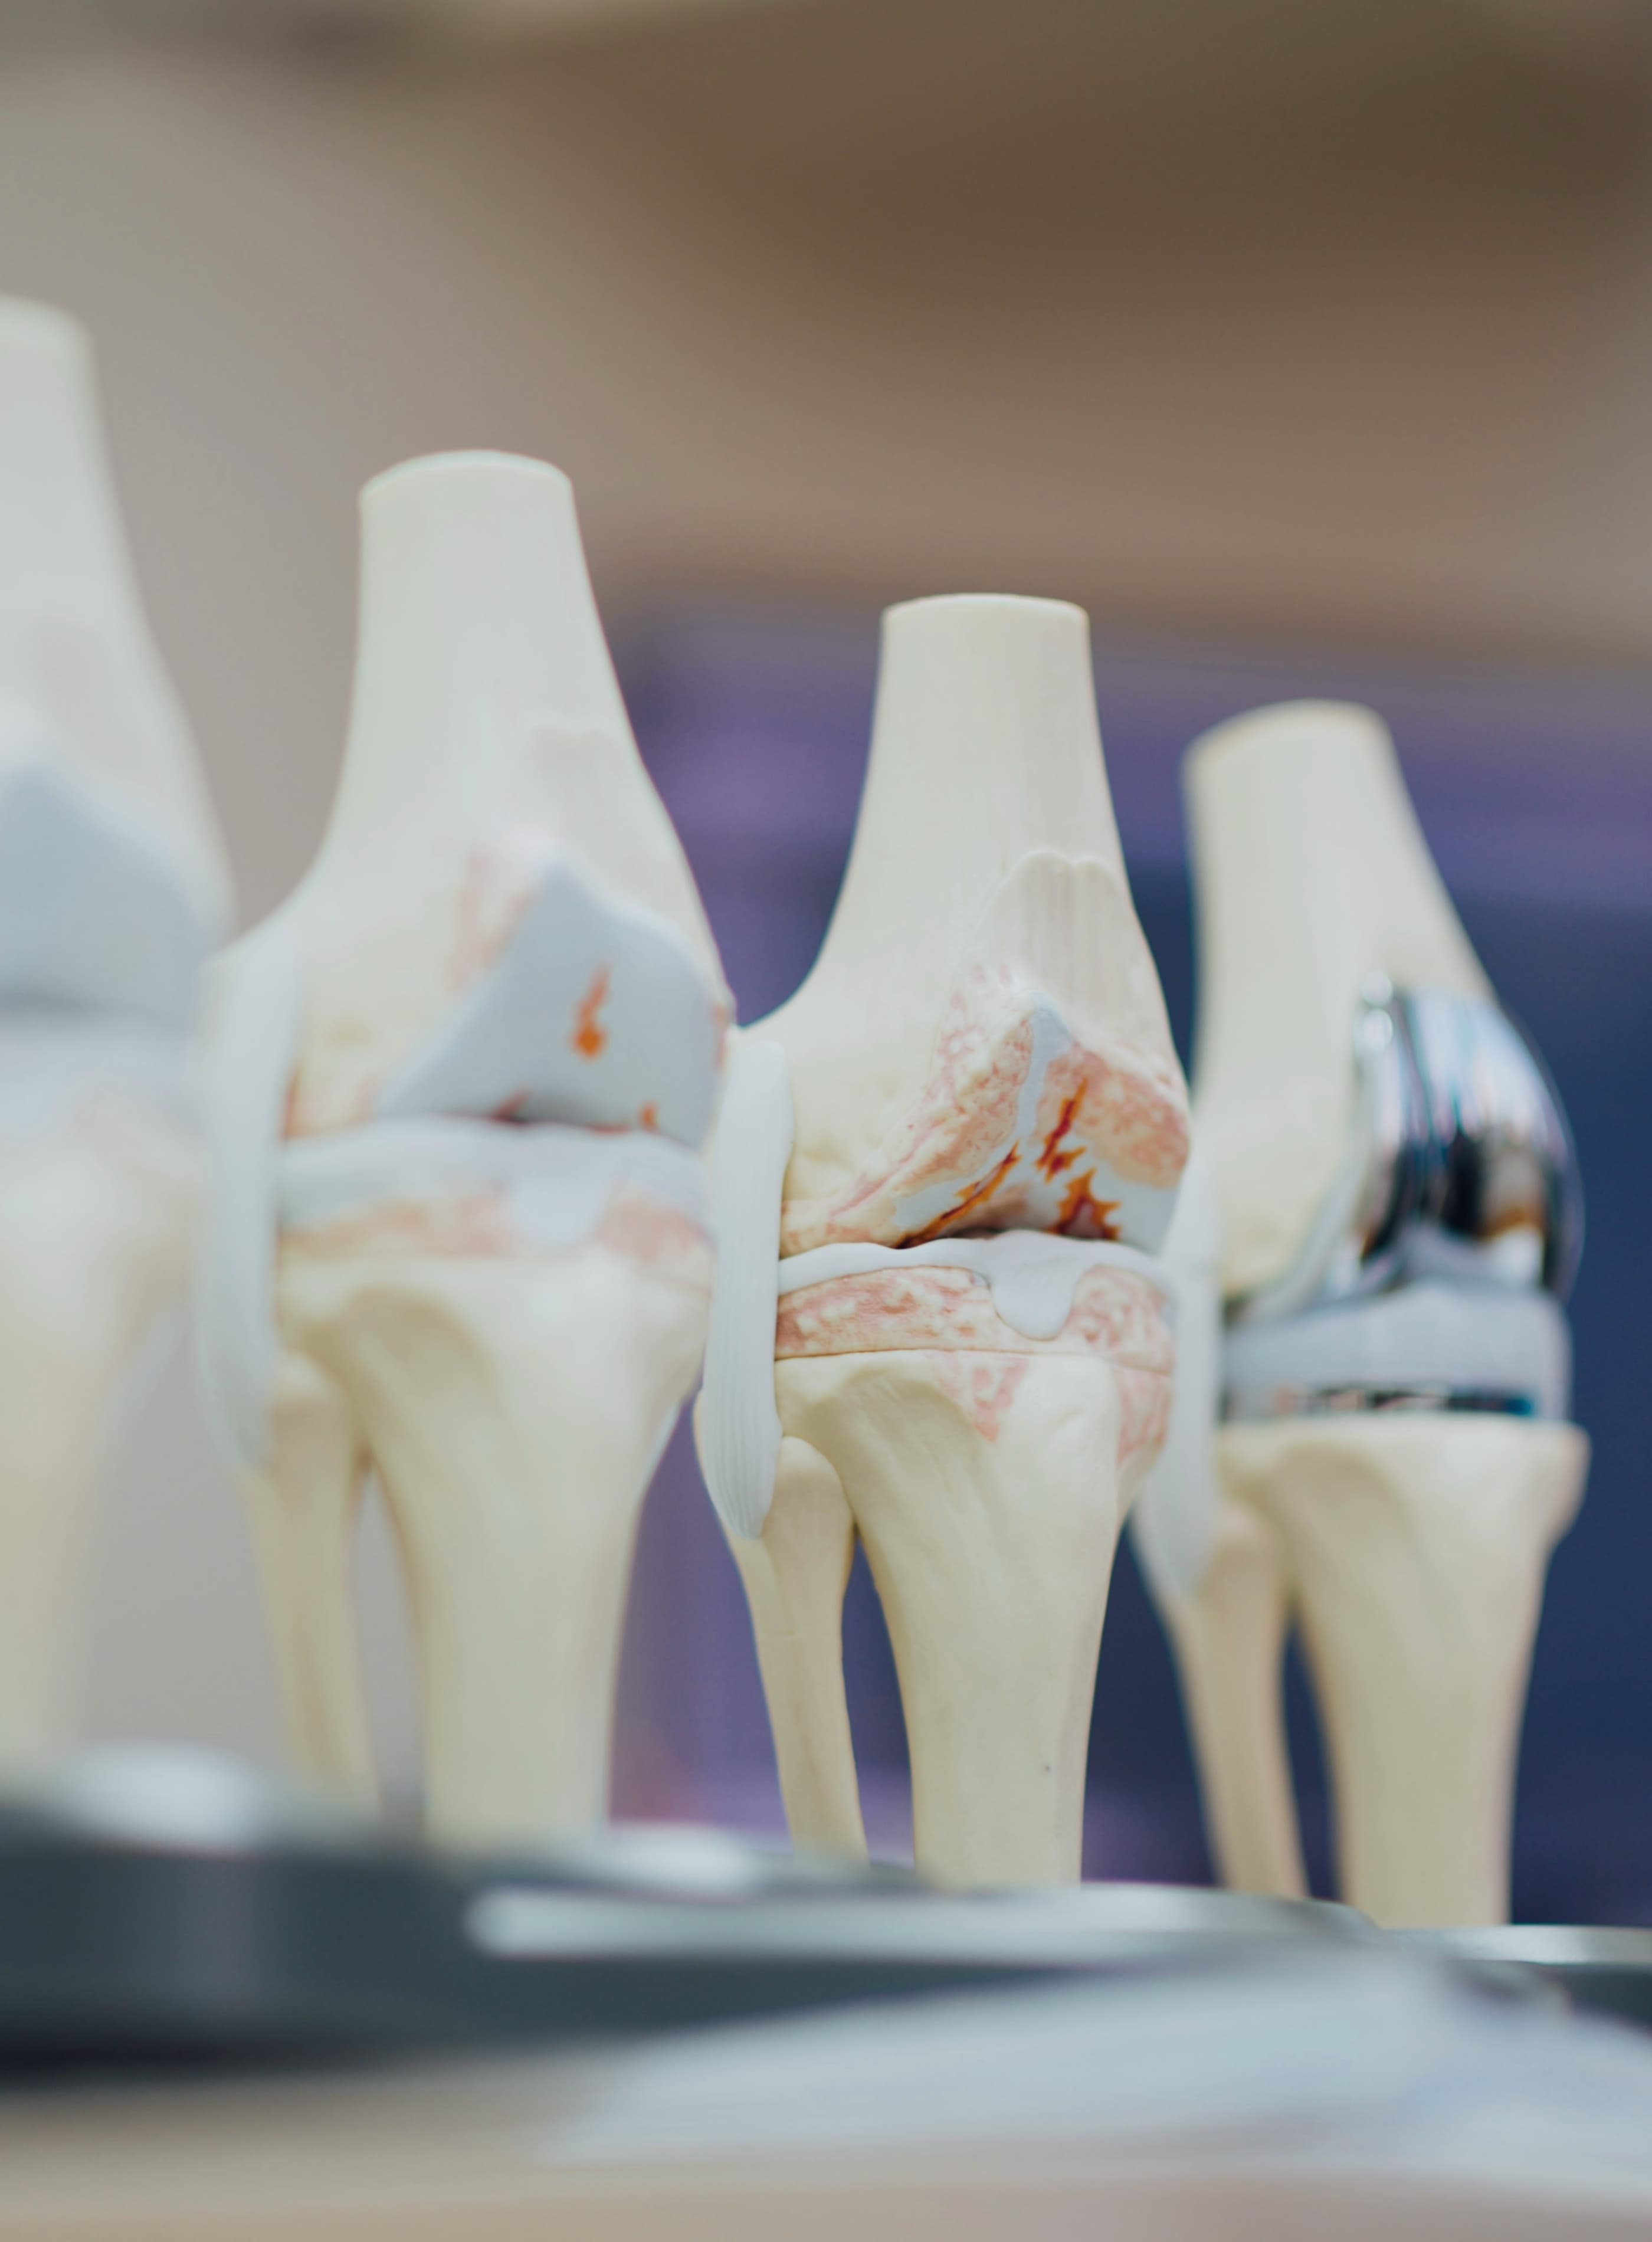
Bone on bone is the everyday term for the most severe X ray grade, Kellgren Lawrence grade 4, where the joint space has gone and there are large bone spurs. It is worth knowing that X ray severity is a poor guide to how much pain or disability someone has: in a systematic review, the proportion of people with X ray arthritis who had pain ranged from 15% to 81% across studies. The treatment ladder is the same at every grade: exercise, weight management, a topical then oral anti inflammatory, a steroid injection for short term relief, and a knee replacement when symptoms substantially affect your life.
Can you live with bone on bone knees without surgery, and can you avoid a replacement?
Yes, many people do. The NHS says surgery is only needed in a small number of cases, and a replacement is recommended when pain is having a big effect on your life and other treatments have not worked, judged clinically rather than by X ray grade. Some people with grade 4 knees manage well for years with strong thigh muscles, a sensible weight and the occasional injection; others with milder X rays are miserable and need surgery sooner. The X ray informs the conversation but does not decide it.
Do I need a knee replacement if my knee is bone on bone?
Not necessarily. NICE says to consider referral when pain, stiffness, reduced function or deformity substantially affect quality of life and non surgical care has not worked, using clinical assessment rather than a scoring system, and not to exclude anyone because of age, sex, smoking, other conditions or BMI, though those affect surgical risk. If the knee is limiting your life despite a proper attempt at the non surgical options, a replacement is the most reliable treatment; if it is not, there is no rush.
What are the treatment options for knee arthritis, in order?
NICE core treatment is therapeutic exercise, weight management if appropriate, and information and support. A topical anti inflammatory gel is first line medication for the knee, then an oral anti inflammatory with a stomach protecting tablet if the gel is not enough. Paracetamol and weak opioids are not routinely offered because the evidence is weak. A steroid injection gives two to ten weeks of relief when other options have failed or to support exercise. Hyaluronic acid, glucosamine, acupuncture and electrotherapy are not recommended. Referral for a knee replacement follows when symptoms substantially affect quality of life despite all of that.
What are good exercises for knee osteoarthritis, and what should I not do?
Land based exercise reduces pain and improves function, with benefit lasting two to six months after a programme ends according to a Cochrane review of 54 trials. Thigh strengthening (sit to stand, step ups, straight leg raises), brisk walking, cycling, swimming and water based exercise are all suitable, and structured programmes such as ESCAPE-pain improve function. Expect some discomfort when you start; NICE says that is normal and that regular exercise reduces pain in the long run. What not to do is too much too quickly, or nothing at all, because rested muscles waste and stiffness increases.
Can walking help knee arthritis, and is walking good for bone on bone knees?
In a study of people aged 50 and over with knee osteoarthritis, those who walked for exercise were less likely to develop new frequent knee pain and showed somewhat less narrowing of the joint space on X ray. Brisk walking strengthens the leg muscles. The study included people with established arthritis, though it was observational and did not test walking specifically in grade 4 knees. In advanced disease a walking stick in the opposite hand and pacing your distance make it more comfortable.
What is the best exercise for bone on bone knees?
The same as for knee arthritis generally: thigh strengthening, cycling, swimming or water based exercise, and walking as tolerated, ideally within a supervised programme at first. The evidence is for knee osteoarthritis as a whole rather than grade 4 specifically, but there is no reason to think advanced knees respond differently to stronger muscles.
Does knee arthritis ever go away?
No. It is a long term condition and cannot be cured, but symptoms fluctuate, and Versus Arthritis notes that in some people the condition peaks after a few years and symptoms stay the same or even ease. The NHS says symptoms can be mild and come and go, often in episodes related to activity and sometimes the weather.
Are there foods to avoid with arthritis?
Versus Arthritis is clear that there is no scientific evidence that cutting out particular foods, such as citrus fruit or tomatoes, helps osteoarthritis, and no diet cures it. What does help is a healthy weight: NICE says losing 10% of body weight is likely to be better than 5%, and in the IDEA trial diet plus exercise, with around 10% weight loss, gave less pain and better function than exercise alone. A Mediterranean style diet is reasonable general advice.
What injection options are there for knee arthritis, and what are the downsides?
A steroid injection is the only injection NICE recommends, for short term relief of two to ten weeks when other treatments have failed or to support exercise. A Cochrane review found the benefit moderate at one to two weeks, small by three months and gone by six. Hyaluronic acid injections are not recommended by NICE. Arthrosamid, a permanent hydrogel injection, has follow up data to five years and is discussed on its own page; it is self pay and not assessed by NICE. The risks of any knee injection include infection and a temporary flare, and a steroid injection within three months of a planned knee replacement is best avoided because of a higher infection risk.
What is classed as severe osteoarthritis?
On X ray, severe means Kellgren Lawrence grade 4. Clinically, NICE deliberately avoids numerical severity scores and defines the point for surgical referral as symptoms substantially affecting quality of life despite non surgical care. The NHS describes severe cases as those where symptoms are continuous rather than episodic.
Can knee arthritis cause pain down the leg?
Knee arthritis pain is usually felt in and around the knee. Pain running down the leg is more typical of a nerve or back problem. A Baker's cyst behind an arthritic knee can cause calf pain or swelling, and a burst cyst can cause sudden calf pain that mimics a clot. Conversely, a hip problem can send pain down the front of the thigh to the knee. Persistent pain radiating along the leg should be assessed.
How do I cope with knee osteoarthritis day to day?
Keep moving with tailored exercise, manage your weight, use a stick on bad days, apply heat or cold, and use an anti inflammatory gel. A structured education and exercise programme such as ESCAPE-pain improves function. Long term pain lowers mood and disturbs sleep, and it is worth saying so to your GP or physiotherapist rather than putting up with it.
Can I claim PIP for osteoarthritis?
PIP is not awarded for a diagnosis but for how much difficulty you have with daily living and mobility tasks, most of the time, where those difficulties are expected to last at least 12 months. People with osteoarthritis can qualify if their function is affected enough. In Scotland the equivalent is Adult Disability Payment. GOV.UK has the eligibility details.
Sources
NICE NG226, Osteoarthritis in over 16s: diagnosis and management (October 2022). https://www.nice.org.uk/guidance/ng226
NHS.uk, Osteoarthritis: symptoms and treatment (reviewed March 2023). https://www.nhs.uk/conditions/osteoarthritis/
NHS.uk, Knee replacement: why it's done (reviewed September 2026). https://www.nhs.uk/conditions/knee-replacement/
Versus Arthritis, Osteoarthritis of the knee; Diet and arthritis. https://www.versusarthritis.org
Fransen M et al. Exercise for osteoarthritis of the knee. Cochrane Database of Systematic Reviews 2015, CD004376.
Jüni P et al. Intra-articular corticosteroid for knee osteoarthritis. Cochrane Database of Systematic Reviews 2015, CD005328.
Lo GH et al. Association between walking for exercise and symptomatic and structural progression in individuals with knee osteoarthritis. Arthritis Rheumatol 2022;74:1660-7.
Bedson J, Croft PR. The discordance between clinical and radiographic knee osteoarthritis: a systematic search and summary of the literature. BMC Musculoskelet Disord 2008;9:116.
Messier SP et al. Effects of intensive diet and exercise on knee joint loads, inflammation, and clinical outcomes among overweight and obese adults with knee osteoarthritis (IDEA). JAMA 2013;310:1263-73.
Hurley MV et al. Clinical effectiveness of a rehabilitation program integrating exercise, self management, and active coping strategies for chronic knee pain (ESCAPE-knee pain). Arthritis Rheum 2007;57:1211-9.
Bannuru RR et al. OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis Cartilage 2019;27:1578-89.
GOV.UK, Personal Independence Payment eligibility. https://www.gov.uk/pip/eligibility